Reading Time: mins
Stem cell injections are injections of cell-containing material, usually taken from your own fat or bone marrow, into a painful joint or tendon. The aim is to ease pain and support the surrounding tissue. These injections are not a cure for arthritis, and the research is still mixed, so who they suit matters a great deal.
In this guide we explain what the term covers, what these injections are used for, what the evidence shows and what to ask any clinic before you book. We are open about the limits, because that is how you can judge whether treatment at RRMG is right for you.
“Stem cell injection” is a broad phrase, and clinics use it for quite different things. Some products are processed from your own tissue on the day. Others are made in a laboratory. Some injections sold under the same label contain very few stem cells at all. So the first useful step is to ask what is actually in the syringe.
The label also hides a difference in source. Autologous material comes from your own body, so there is nothing to match. Allogeneic material comes from a donor, and some products are grown or modified in a laboratory. Each type carries different rules, different risks and different evidence. When you read a clinic’s description of its stem cell injections, look for a plain statement of which type it uses and where the tissue comes from.
Stem cells are cells that can renew themselves and develop into other cell types. In orthopaedics, the idea is that injecting them near a worn joint or damaged tendon may calm inflammation and help the tissue around it. That is a hope supported by laboratory work. It has not been shown to rebuild a worn joint in people.
In joint and tendon care, the material most often comes from you. Fat tissue and bone marrow both contain cells that researchers describe as mesenchymal stem or stromal cells. Because the material is your own, it avoids the matching problems of donor tissue.
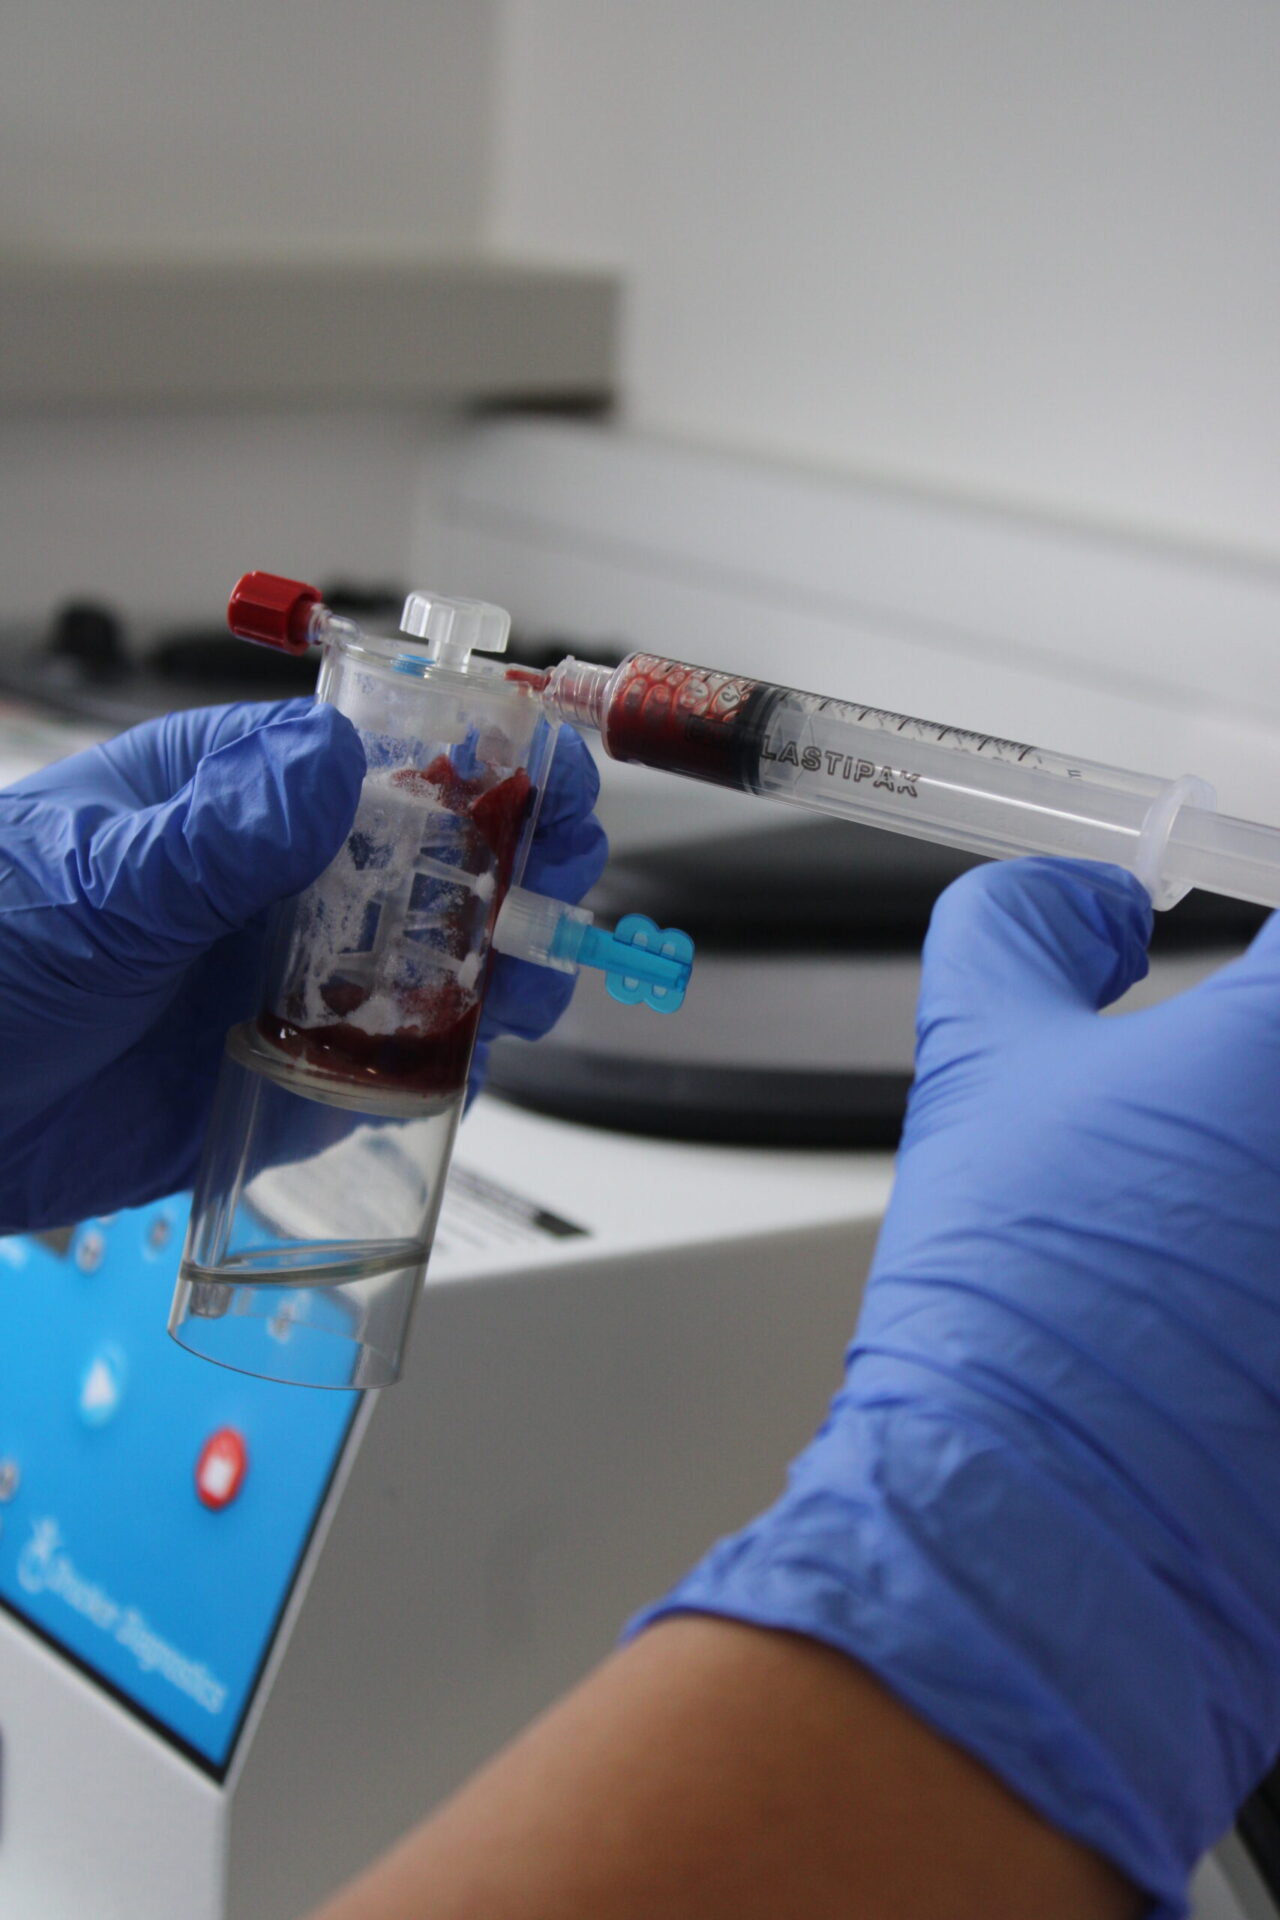
At RRMG, our Lipogems treatment uses a small amount of your own fat, processed in a closed system and injected into the treatment area. Our PRP injections and Cellular Matrix treatments are different. Both are made from your blood, so neither is a stem cell treatment, and we say so plainly.
Stem cells are useful in science because they can release signals that influence inflammation and repair. That has made them attractive for conditions where tissue slowly wears down. What remains unproven is how much of that effect carries over to a real patient’s knee, and whether it lasts. Good laboratory results do not always become clear clinical benefit.
In orthopaedics, stem cell therapy is mainly used for painful joints and tendons that have not settled with sensible first steps. Where are stem cells used for joint problems most often? In osteoarthritis, tendon injuries and some soft tissue problems. So what can stem cell treatment be used for in practice? Mostly to ease pain and improve movement, not to replace damaged tissue. The stem cell injections purpose in our clinic is exactly that: symptom relief that lets you move and rehabilitate more comfortably.
We treat these injections as one option among several, and never as the first step for everyone. You can see the wider range of non-surgical treatments and the conditions we treat on our website.
Arthritis is the most common reason people ask us about stem cell injections. In osteoarthritis the cushioning cartilage thins and the joint becomes sore and stiff. An injection may help calm that irritation for some people, and studies suggest results tend to be better in milder to moderate disease than in very advanced joints. Doctors usually grade knee arthritis on X-ray from grade 1 (very mild) to grade 4 (severe), and we use that grading, along with MRI or ultrasound where needed, to judge whether an injection is a sensible next step.
It is important to be clear about what an injection cannot do. It does not reverse arthritis or grow back lost cartilage. Where a joint is badly worn, other options, including a surgical opinion, may be more reliable.
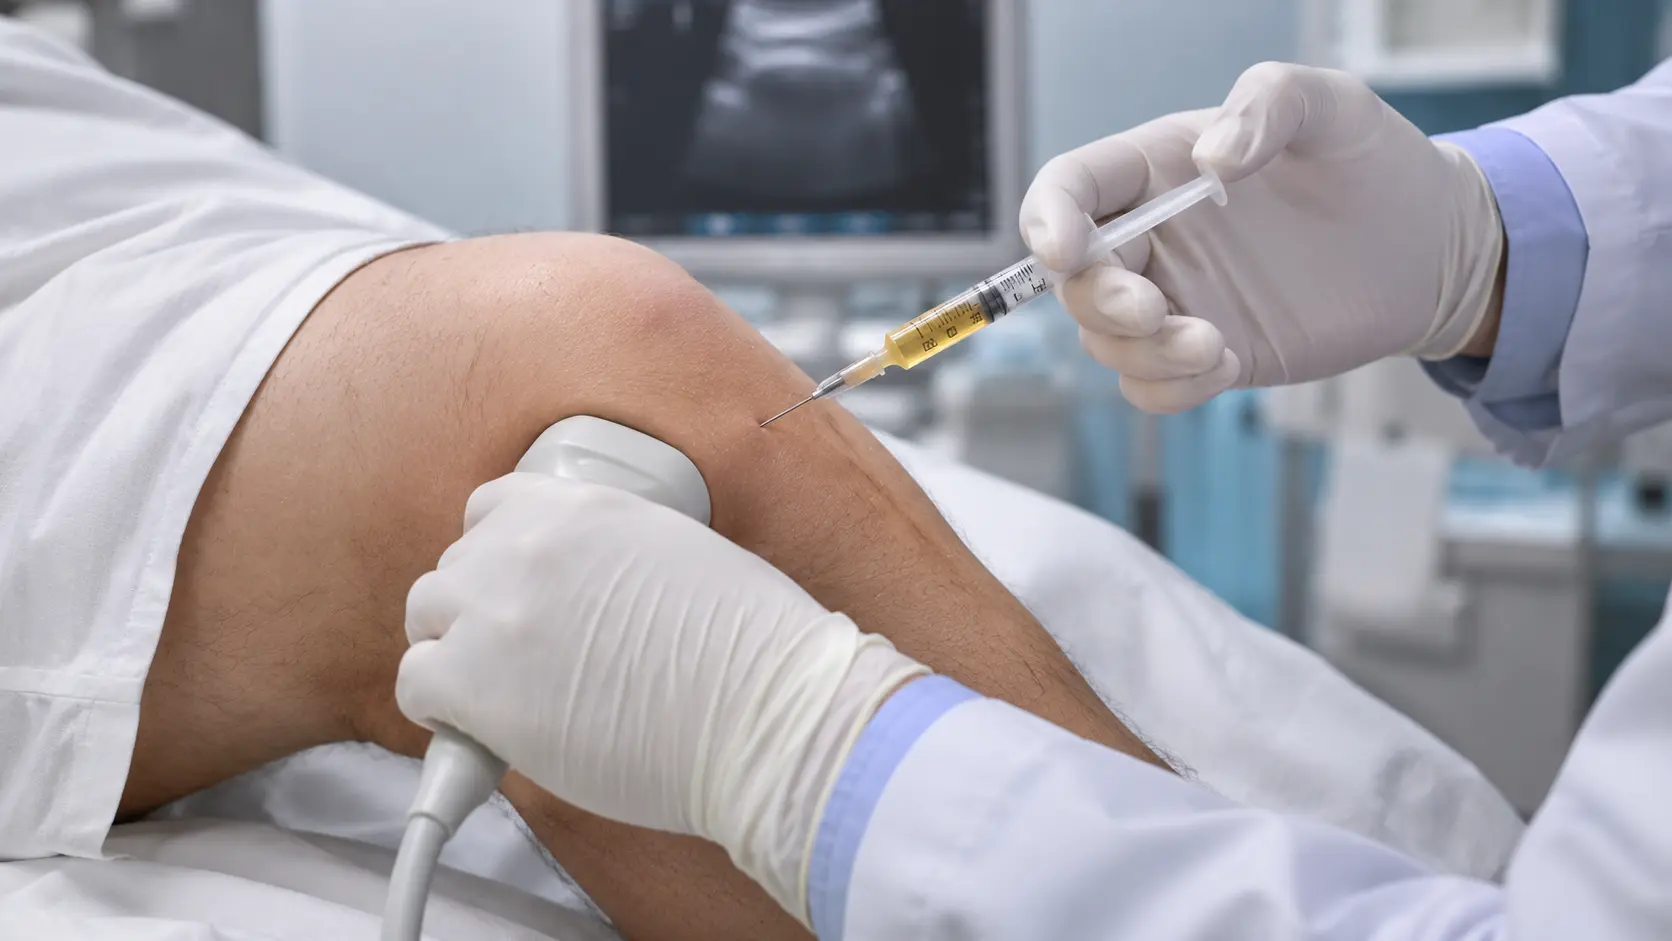
The knee is where most of the research sits. If you are asking what are stem cell injections for knees, the answer is a single injection of processed fat or marrow tissue into the joint, usually guided by ultrasound. We first confirm that the pain is coming from the joint itself, since knee pain is sometimes referred from the hip or back, or comes from a tendon or a meniscal tear. Alignment matters too. A knee that is badly bowed or unstable is under uneven load, and an injection does not correct that. Our knee osteoarthritis care page explains how we assess it.
The hip sits deep in the body, so accurate placement matters. We use image guidance for the injection, and we check the hip is the true source of pain, because problems in the lower back or around the hip tendons can feel similar. As with the knee, the injection is aimed at easing symptoms in a joint that has worn, not at reversing the wear. More detail is on our hip arthritis care page.
For the shoulder, injections are mostly considered for arthritis and for tendon problems such as rotator cuff irritation that has not settled. We examine the shoulder, use ultrasound to look at the tendons and then decide whether an injection or another approach makes more sense. For some tendon problems a blood-based option such as PRP may be considered before anything else. Our shoulder pain care page covers how we assess these.
Do stem cell injections work? For some people they may ease pain, but the best controlled evidence we found showed no advantage over a saline injection in knee osteoarthritis. Results vary from person to person, and no clinic can promise a particular outcome. That honest picture should guide any decision.
Many early studies were case series, which follow patients after treatment but have no comparison group. Many report improvement in pain and function. The difficulty is that a placebo response and the natural ups and downs of arthritis can account for part of that gain, and a case series cannot separate them. Arthritis symptoms rise and fall over time, and people often seek treatment when they are at their worst, so some improvement would be expected anyway.
Controlled trials are more cautious. A blinded randomised trial in the British Journal of Sports Medicine enrolled 120 adults, with an average age of about 52, who had knee osteoarthritis of grade 2 to 3 on X-ray. Half received a single injection of their own micro-fragmented fat and half received saline, and the team followed everyone for two years. Both groups improved, but the fat injection did not do better than saline at any follow-up point. Each injection held roughly a million stem cells, yet that did not translate into extra benefit. This is one trial in one type of patient, so it does not settle the question, but it is the best controlled evidence we found. We cover how this evidence shapes who we offer treatment to in our post on Lipogems treatment planning.
The benefits people hope for are less pain, easier movement and a longer gap before surgery is considered. Some patients report these gains. The limits matter just as much. The effect may fade, it varies between people, and the best controlled trial we found showed no advantage over saline.
That is why we do not describe any injection as a way to avoid surgery. We describe it as one option that may help certain patients.
What this means for you is simple. Treat any promise of a guaranteed result with caution, ask to see the evidence behind a claim and expect a clinic to tell you what is uncertain as well as what is encouraging. If you decide to go ahead, a sensible plan pairs the injection with rehabilitation and a clear follow-up, so you and the clinician can judge its effect together.
In the UK, cell-based treatments are regulated. The MHRA classes some of these products as advanced therapy medicinal products, and they generally need a marketing authorisation, with limited exceptions such as the hospital exemption for specific patients. In practice this means the exact product, how it is made and where it is used all matter. The rules are detailed, and the advertising regulator has also ruled against stem cell adverts where the evidence did not support the claims. In practice, stem cell injections in the UK are offered mainly by private clinics, and the products and processes behind them differ a great deal from one provider to the next. That is why the questions below matter more than a brand name or a price. A good clinic will explain its position clearly, in language you can follow, and will not treat a fair question as an awkward one.
Questions worth asking any provider before you book:
If a clinic cannot answer these plainly, or promises certain results, treat that as a reason to pause.
Our London clinic is on Blythe Road, and we use image guidance for every injection. Your first visit is an assessment, not a procedure. Please bring any previous scans, X-ray reports and a list of your medicines, so we can build a complete picture from the start. We review your history and scans, examine the joint and talk through whether treatment makes sense. Our approach draws on founder Dr Ralph Rogers’s years of image-guided musculoskeletal work, and you can read more about RRMG on our website.
If Lipogems is appropriate, it is done as a day case under local anaesthetic. A small amount of fat is taken, processed and injected, and the whole visit usually takes 60 to 90 minutes. Expect some soreness, swelling or bruising for a few days. Most people return to normal daily activity within one to two weeks, and improvement is usually noticed over the following two to eight weeks, although this varies. Physiotherapy often works alongside the injection, and we may advise easing back into sport gradually in the first few weeks. Fat is commonly collected from the abdomen, so you should expect a small tender area there as well as at the treated joint. We explain aftercare in detail at the time and arrange a follow-up so we can see how you are responding.

Stem cell injections may suit some adults whose joint pain has lasted and not settled with first-line steps. We consider the whole picture, not one test result. Features that generally point towards a good fit include:
Some factors call for more caution, including blood-thinning medicines, an active infection, uncontrolled medical conditions and a joint that is badly misaligned or unstable. At assessment we will tell you plainly if another route looks better for you. None of these automatically rules treatment out, but they change how we plan or whether we advise a different route. Never stop a prescribed medicine without medical guidance.
Other options may suit you better in some cases. PRP is a less invasive blood-based choice for milder problems, and a surgical opinion may be right for a badly damaged joint. Our comparison of PRP versus stem cell therapy sets out the differences.
If joint pain is limiting what you can do, a consultation is the way to find out whether a stem cell injection makes sense. It does not commit you to treatment.
RRMG is a private regenerative orthopaedics and sports medicine clinic on Blythe Road, London, and we personally run every case, drawing on founder Dr Ralph Rogers’s image-guided experience. We work with a wide range of insurance providers as well as self-funding patients.
With us, you get fast access to a specialist assessment without joining a long waiting list, a clear diagnosis instead of continued guesswork, and a plain explanation of what treatment can and cannot do. Booking is simple: call, email or use our contact form, and we will arrange your first visit. Our aim is simple: to match the right option to you, whatever that turns out to be.
| Service | Indicative Price |
| Initial consultation | From £300 |
| Lipogems, one joint | From £6,500 |
| Lipogems, two joints | From £9,500 |
Please visit our fees page for current, exact pricing.
You can book a consultation with us today:
Painful is relative, and it differs from person to person. We use local anaesthetic, so you may feel pressure more than sharp pain. Soreness or bruising at the joint and, with Lipogems, at the fat collection site is common for a few days. We talk you through what to expect before any procedure so there are no surprises.
Using your own tissue avoids rejection problems, but any injection carries some risk, including soreness, swelling, bruising and, rarely, infection. Safety also depends on the product, the clinic and your health, including medicines such as blood thinners. We review all of this at your assessment before advising treatment.
There is no fixed answer. Some people notice benefit for many months, and for others it fades sooner or never appears. Research on how long the effect lasts, and on repeat injections, is still limited. We discuss what is sensible for you if symptoms return.
No. PRP (platelet-rich plasma) is made from your blood and concentrates platelets. Stem cell injections, such as Lipogems, use your own fat tissue. Both are regenerative options with different sources, costs and evidence, so the right choice depends on your joint and your goals.
Stem cell injections for joint pain are generally a private treatment and are not part of routine NHS care. The NHS usually offers other steps first, and may offer steroid injections when other treatments have not worked. We can explain how the options compare at consultation.
Dr Rogers has had a rich and illustrious career so far, which is continuing to grow and develop. Everything Ralph has been involved in since qualifying has added value to his knowledge and experience, but there have been some impressive highlights to note:
2018 – Present Founder Medical Director: Rogers Regenerative Medical Group (RRMG)
2012 – 2024 Medical Advisor – National Basketball Association
2008 – 2018 Medical Director: The London Sports Injury Clinic London
2010-2011 First Team Doctor, Chelsea Football Club
2007- 2010 The Football Association (Team Physician for England under 19 and development squads)
2005-2006 Medical Advisor: Trinidad & Tobago World Cup Football Team
2002 – 2008 Club Doctor: Walsall Football Club, West Midlands England
1998 – 2009 Medical Director: Medical & Orthopaedic Sports Therapy,
2000 – 2005 Sports Physician: Warwickshire County Cricket Club, Birmingham