Reading Time: mins

Sciatica or Facet Joint Pain? Identifying the source of your pain is important for choosing the right injection.Back pain that spreads into the buttock or leg is often called sciatica, but that label is not always right. Sciatica is pain from an irritated spinal nerve, usually a sharp, burning or shooting pain that travels below the knee, sometimes with tingling, numbness or weakness. Facet joint pain comes from the small joints at the back of the spine. It is usually a deep ache in the lower back that can spread into the buttock and upper thigh, and it can look very much like sciatica.
The difference matters because the injections used for each problem work in different places and for different reasons. In the sciatica vs facet joint pain question, the source of the pain decides which injection, if any, makes sense. An injection aimed at the wrong place is unlikely to help, so we start with the source and only then talk about treatment.
In this guide we explain how the two conditions differ, why they are so easy to confuse, how doctors work out which one you have, and what the injection options offer in practice. It is general information, not a diagnosis, and it cannot replace an assessment of your own back.
The table below shows the patterns we usually look for. They are guides, not rules, and many people have features of both.
| Sciatica (nerve pain) | Facet joint pain | |
| Where it starts | Lower back or buttock, then follows a nerve down the leg | Lower back, often more on one side |
| How far it spreads | Often below the knee, sometimes to the foot | Usually the buttock or upper thigh, less often below the knee |
| What it feels like | Sharp, shooting, burning or electric | Deep ache and stiffness |
| Other nerve symptoms | Tingling, numbness or weakness can occur | Not typical, so these point towards a nerve |
| Often worse with | Sitting, bending, coughing or sneezing | Twisting, leaning backwards, long standing, or getting up from a chair |
| Common cause | A prolapsed disc or narrowing around a nerve | Wear and strain in the joints |
| Injection that may be considered | Epidural or nerve root injection, in selected cases | A medial branch block to test the joint, then radiofrequency treatment in selected cases |
The symptom lists for each column come from the way we describe sciatica and facet joint pain when assessing patients, and the key point is the overlap in the middle: a buttock or thigh ache could belong to either.
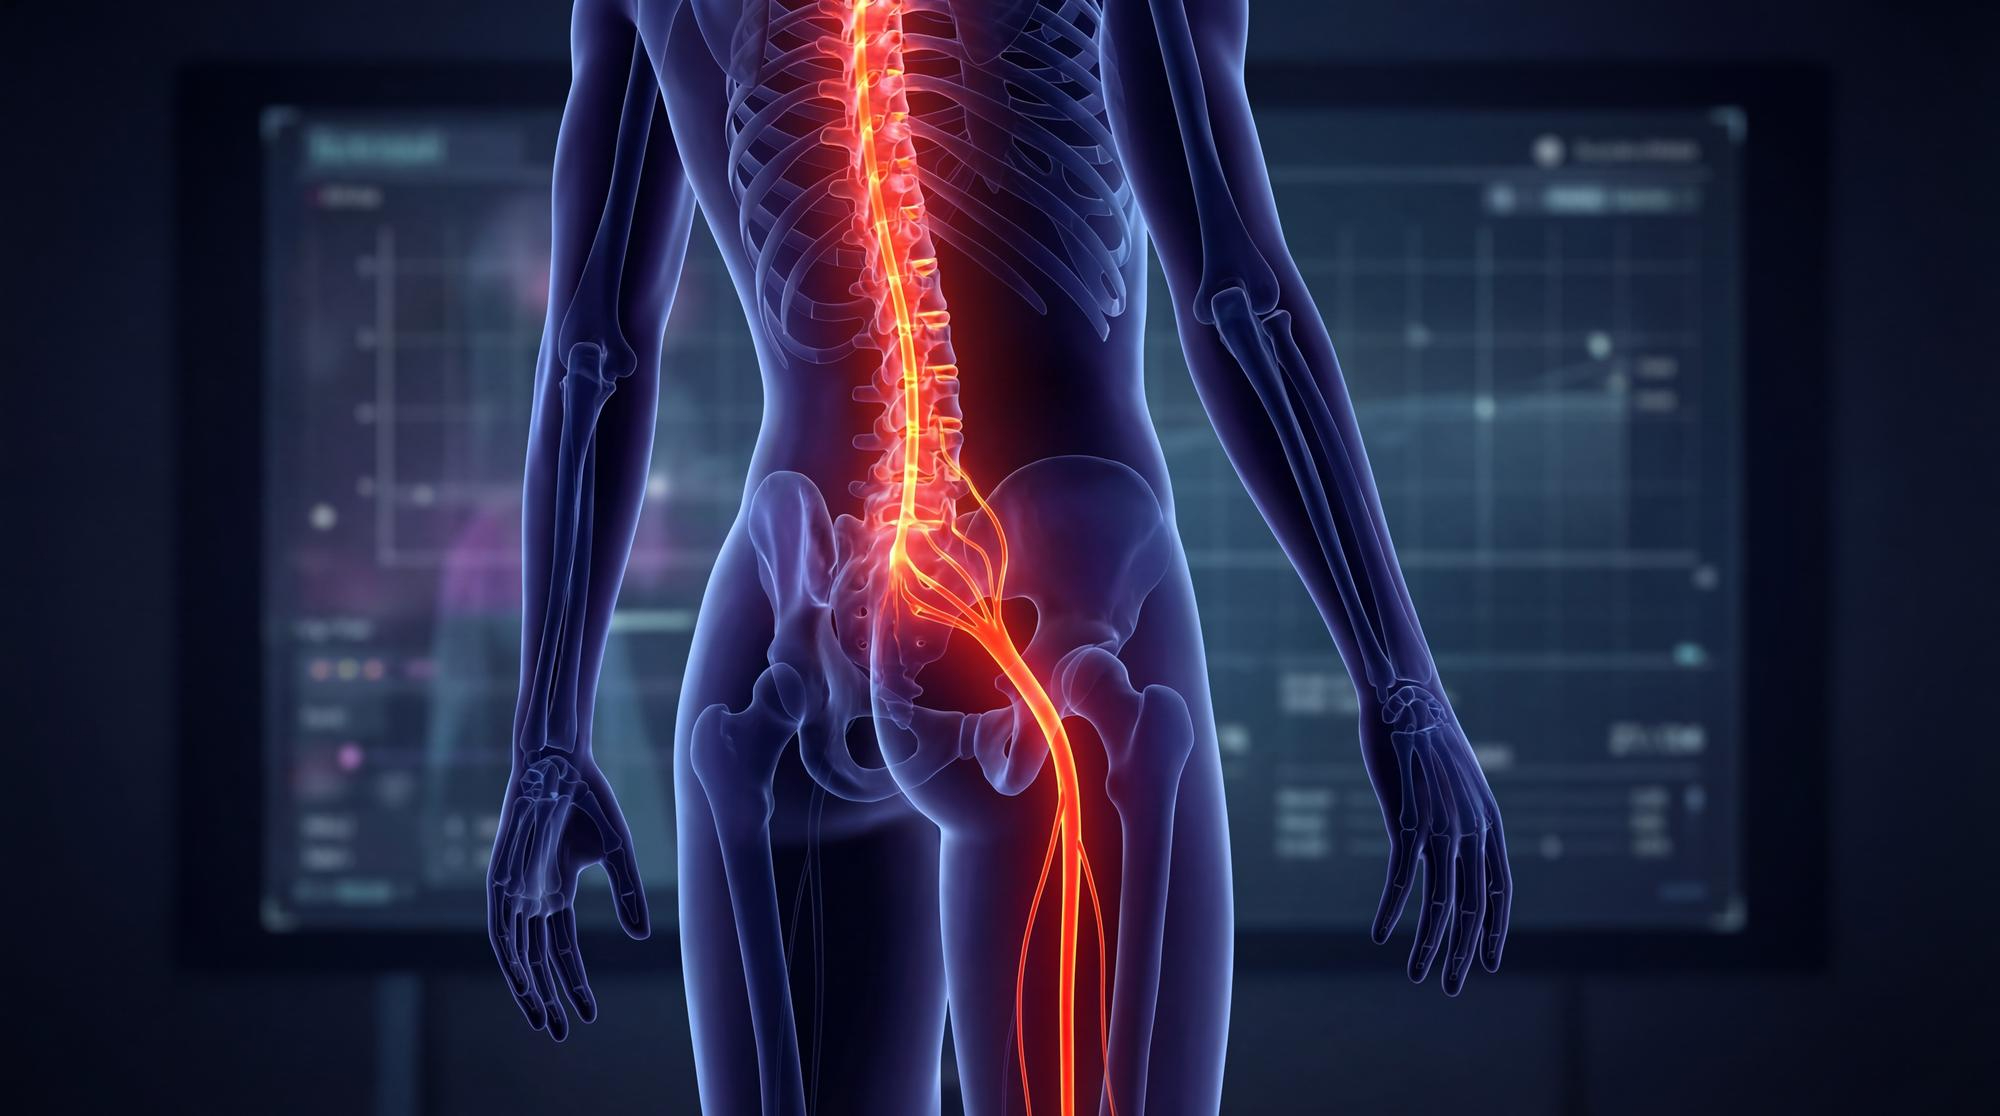
Sciatica describes pain that travels along the sciatic nerve from the lower back, through the buttock and down the leg. It is a symptom rather than a diagnosis. It develops when a nerve in the lower spine becomes irritated or compressed, most often by a disc that has bulged or prolapsed, or by narrowing of the small openings or the central canal through which the nerves pass.
Sciatica is common, and the outlook is usually better than people fear. A review in the British Journal of Anaesthesia estimates a lifetime incidence of between 13% and 40%, and notes that most cases settle on their own with simple pain relief and physiotherapy. That is why a scan or an injection is not the first step for everyone.
Scan findings need care too. Wear and tear in the lower spine is common and does not always cause pain, so changes seen on an MRI have to be read alongside your symptoms and examination.
The facet joints sit in pairs at the back of each spinal level and guide movement when you bend, twist and lean back. When they become worn or irritated, they can cause a deep ache in the lower back, stiffness after sitting, and discomfort when twisting, leaning backwards or standing for long periods.
The reason facet pain is mistaken for sciatica is that these joints share nerve supply with the buttock and thigh. Pain from a lower lumbar facet joint can be felt in the buttock and upper thigh even though the joint itself is in the spine. This is called referred pain. It is usually duller and less sharp than nerve root pain, and it is less likely to travel below the knee. When pain does travel further, particularly with tingling, numbness or weakness, we look harder for nerve involvement or another cause.
Pain that flares mainly when you twist or lean back fits the classic pattern of facet joint pain, and it is one of the first clues that the joints may be involved.
There are three reasons the symptom pattern is not enough on its own.
First, the patterns overlap. A facet joint, a nerve root and the sacroiliac joint can all produce a deep ache in the buttock. If your lower back pain is worst when getting out of a car or rolling over in bed, the sacroiliac joint may be involved too, and back pain when getting out of the car is one of its typical signs.
Second, more than one structure can hurt at once. A worn disc, irritated facet joints and an irritated nerve often appear together, and treating only one may leave the others untouched.
Third, scans do not settle the question. An MRI can show degenerative changes in the facet joints, but those changes do not prove the joints are the source of your pain. In the same way, a disc bulge on a scan does not prove it is the cause of your leg symptoms. That is why we interpret imaging alongside your history and examination rather than on its own.
The assessment starts with your story: where the pain began, what it feels like, how far it travels, what makes it better or worse, and what treatment has already been tried. We then examine your back, hips and legs, checking movement, strength, sensation and reflexes, and we look at which movements and positions reproduce your pain. The pattern across several findings is more useful than any single test, an approach shaped by founder Dr Ralph Rogers’s years of image-guided musculoskeletal assessment.
MRI is not needed for everyone. It is most useful when persistent symptoms, a suspected serious cause or a planned procedure means the result could change what we do. Where it is needed, we review it together with your examination.
When the picture is still unclear, a diagnostic injection can help. A small amount of local anaesthetic placed next to a nerve root or the nerves supplying a facet joint shows whether numbing that structure reduces your usual pain. It is a test of where the pain comes from, and the result is interpreted with care because relief can also come from placebo response or resting after the procedure. If your pain has been hard to pin down, you can book a consultation and we will go through your history, examination and any scans with you.
An epidural steroid injection places anti-inflammatory medicine and local anaesthetic around an irritated nerve root, using image guidance. One approach, the transforaminal injection, goes through the small opening where the nerve leaves the spine. The aim is to calm inflammation around the nerve so the leg pain eases enough for you to move and rehabilitate more comfortably. It’s one of the lower back spinal injections we offer.
In the UK, NICE, the National Institute for Health and Care Excellence, guideline NG59 says epidural injections of local anaesthetic and steroid can be considered for people with acute and severe sciatica. It also advises against epidural injections for neurogenic claudication, leg symptoms on walking, caused by narrowing of the central spinal canal.
The evidence on how much they help is mixed and worth knowing before you decide. A UK trial published in Health Technology Assessment found a short-lived benefit at three weeks compared with placebo, with no difference between weeks 6 and 52 and no difference in the need for surgery. A 2024 meta-analysis in Frontiers in Neurology concluded that epidurals help sciatica caused by disc herniation in the short to medium term, while noting that their effectiveness remains debated. Taken together, an epidural is best seen as a way to reduce severe pain for a period, not a cure.
That makes selection important. An epidural may be reasonable if you have severe leg pain that follows one nerve, symptoms and examination that point to the same nerve root, and pain that has not settled with time, medication and physiotherapy. It is less likely to help if your pain is mainly in the back and buttock, which is the more typical picture for facet joint pain. A specialist assessment can help determine whether this procedure may be appropriate for you.
Two different procedures are often grouped together under facet joint pain treatment, and it helps to separate them.
A medial branch block numbs the small nerves that carry pain signals from a facet joint. Its main job is diagnostic: if your usual pain falls clearly while the anaesthetic is working, the joint is more likely to be an important source. A diagnostic medial branch block is not designed to be a lasting treatment, and the result has to be recorded carefully because relief can have other explanations.
A facet joint injection places anaesthetic and steroid into or around the joint itself. NICE does not recommend spinal injections for managing low back pain, so we discuss the evidence and your alternatives openly before suggesting one, and we do not present it as a standard fix.
The positive block has a purpose. NICE advises that radiofrequency ablation for chronic low back pain should only be performed after a positive response to a diagnostic medial branch block. It uses controlled heat to interrupt the same small nerves for a period, typically months rather than years, and the nerves can regrow. The research on it is mixed, and careful selection is one of the main reasons results differ between studies. For many people, exercise and rehabilitation do as well, and we only consider a procedure when the clinical findings and treatment history support it.
This table summarises how the suspected source influences the choice. It describes what may be considered after assessment, not what any one person should have.
| Suspected source | Procedure that may be considered | What it is for |
| Irritated nerve root (sciatica), acute and severe | Epidural or nerve root injection | Short-term reduction of leg pain to allow recovery |
| Facet joint, source unclear | Diagnostic medial branch block | Testing whether the joint is the pain source |
| Facet joint, confirmed by a positive block and not helped by other treatment | Radiofrequency ablation | Longer interruption of pain signals from the joint |
| Sacroiliac joint | Assessment for the sacroiliac joint | Separating it from facet and nerve pain |
| Unclear or mixed | Further examination, review of scans, diagnostic injection | Narrowing down the source before any treatment |
When the sacroiliac joint is the suspected source, assessment usually starts the same way, with a focused history and examination, sometimes followed by its own diagnostic injection into the joint, before any treatment is planned. We can work through this as part of a wider assessment when your pain doesn’t fit neatly into either the sciatica or facet joint pattern described above.
The comparison of facet joint injection vs epidural steroid injection therefore comes down to one question: is the pain coming from the nerve or from the joint? An epidural treats the nerve root. A medial branch block tests the joint. Neither is a substitute for the other.
Spinal injections are generally safe when performed with image guidance by an experienced clinician, but they are not risk free and they do not suit everyone. The common effects are soreness or bruising where the needle went in and a temporary rise in your usual ache once the anaesthetic wears off. Steroid injections can cause temporary flushing and can raise blood sugar for a few days in people with diabetes. Less common problems include a headache after an epidural, a short spell of numbness or faintness, and, rarely, infection, bleeding or nerve injury. Bleeding risk is higher if you take blood-thinning medicines, so tell your doctor about everything you take.
The main limit is that injections address pain, not the underlying wear or disc change. Relief varies from person to person and is often temporary. No injection can be guaranteed to work, and a consultation does not commit you to having one.
For both sciatica and facet joint pain, rehabilitation and staying active remain the foundation of treatment. Many people improve with time, appropriate activity and a well-designed exercise programme. Injections are best used as a bridge: when pain is severe enough that it stops you moving or taking part in physiotherapy, reducing it for a time can make rehabilitation possible.
If physiotherapy has not helped, the diagnosis and the plan may both need reviewing, and we’re happy to go through the other treatment options available rather than repeating the same approach.
It is worth arranging a specialist assessment if any of the following apply:
Your back or leg pain has lasted more than a few weeks and is not improving. Physiotherapy, medication and activity changes have not helped enough. Pain is limiting your sleep, work or daily activity. You have been told you need an injection but are unsure which one or why. You have tingling, numbness or leg weakness that is persistent or getting worse. Different clinicians have given you different explanations for the same pain.

The right treatment depends on where your pain is coming from, and that is exactly what a careful assessment is for. At RRMG, we go through your symptoms and history, examine your back, hips and legs, and review any scans you have, drawing on founder Dr Ralph Rogers’s years of image-guided musculoskeletal work. We can then explain whether your pain looks more like nerve pain, joint pain or a mixture of the conditions we treat, which options are worth considering, and which are not. Some people need an injection. Many do not, and we will tell you if that is the case.
Our private back pain service is based at 1 Blythe Road, London W14 0HG, and we work with a wide range of insurance providers as well as self-funding patients. An initial consultation starts from £300, and you can check our fees page for current, exact pricing before you commit to anything.
If you would like to understand whether your pain is sciatica or facet joint pain, and what that means for treatment, request an appointment with us today or call +44 (0)207 112 5400.
Pain that follows a line below the knee, feels sharp or burning, and comes with tingling, numbness or weakness points more towards a nerve. A deep, dull ache in the lower back and buttock that is worse with twisting or leaning back points more towards the facet joints. These are clues only, and examination is needed to tell them apart reliably.
For acute and severe sciatica, an epidural or nerve root injection of local anaesthetic and steroid may be considered, and NICE supports this in that situation. It usually gives temporary relief rather than a cure, and it is chosen only after assessment.
A medial branch block is the injection most often used to test whether a facet joint is the source. If the result is clearly positive and other treatment has not helped, radiofrequency ablation may then be discussed. Facet joint injections are used less routinely, and NICE does not recommend spinal injections for managing low back pain.
Not on its own. An MRI can show a disc bulge, nerve compression or joint wear, but these findings also occur in people with no pain. We read the scan alongside your symptoms and examination.
Yes. It is common for more than one structure to contribute, which is one reason a careful assessment matters before any injection.
Not necessarily. Many cases improve with time, activity and rehabilitation. An injection is considered when pain is severe or persistent, other treatment has not worked and the findings support it.
Dr Rogers has had a rich and illustrious career so far, which is continuing to grow and develop. Everything Ralph has been involved in since qualifying has added value to his knowledge and experience, but there have been some impressive highlights to note:
2018 – Present Founder Medical Director: Rogers Regenerative Medical Group (RRMG)
2012 – 2024 Medical Advisor – National Basketball Association
2008 – 2018 Medical Director: The London Sports Injury Clinic London
2010-2011 First Team Doctor, Chelsea Football Club
2007- 2010 The Football Association (Team Physician for England under 19 and development squads)
2005-2006 Medical Advisor: Trinidad & Tobago World Cup Football Team
2002 – 2008 Club Doctor: Walsall Football Club, West Midlands England
1998 – 2009 Medical Director: Medical & Orthopaedic Sports Therapy,
2000 – 2005 Sports Physician: Warwickshire County Cricket Club, Birmingham