Reading Time: mins

If you’re dealing with lower back pain lower left side of your spine, above the buttock and below the ribs, you’re feeling one of the most common reasons people come to see us. Most of the time, this pain is mechanical. That means it’s coming from a joint, disc, or muscle in your lower spine rather than from an internal organ.
You might notice it as back pain lower left side above hip, or feel it sitting more toward the back pain lower left side buttocks area, closer to where your spine meets your pelvis. Either way, the exact spot it settles in gives us a useful early clue about which structure is likely involved.
We want to be honest with you from the start: telling the difference between a few of the likely mechanical causes just from how the pain feels is genuinely hard, even for us. A disc problem, a facet joint problem, and a sacroiliac (SI) joint problem, the joint connecting your spine to your pelvis, can all cause pain in almost exactly the same spot on your left side. A 2023 review of the evidence on this exact question found that ordinary clinical tests, the kind used in a standard exam, could not reliably pick out facet joint pain at all, and needed several tests combined just to flag the SI joint as a likely source. That’s exactly why we don’t rely on guesswork. We use image-guided assessment to see which structure is behind your pain before we recommend any treatment.
This doesn’t mean every case of left-sided back pain needs urgent imaging. It means the “just rest and see” approach, on its own, often leaves you no clearer on what’s wrong weeks later.
A sore lower left back that comes on after sitting for long stretches, an awkward lift, or a night spent sleeping in one position usually points to a muscle strain or an irritated facet joint rather than anything more serious. This is also where you’ll often hear people describe a pulled muscle lower back left side, since a sudden awkward movement is one of the most common triggers we see.
When you sit for hours, especially at a desk angled toward one side, or lift with your spine twisted rather than your legs doing the work, the small facet joints on that side of your lower spine take more load than they’re built for. The result is a dull back pain lower left side that tends to ease a little once you get moving, then tightens up again if you sit still too long. We see this pattern constantly in patients whose left-sided pain started after a specific weekend of gardening, moving furniture, or an unusually long car trip.
If this sounds like your pain, and there’s no numbness, tingling, or pain running down your leg, it’s very likely mechanical and very likely treatable without surgery. What matters is getting an accurate diagnosis early, rather than letting a strain that should settle in weeks turn into a pattern your body compensates around for months.
When lower left back pain starts radiating into your hip, buttock, or down your leg, we’re usually looking at a nerve being irritated or compressed, most often from a disc bulging against it or from sciatica affecting the left side.
A disc that’s pushing on a nerve root tends to cause pain that follows a specific path down the leg, sometimes with pins and needles or numbness along the same route. SI joint irritation, on the other hand, more often stays closer to the hip and buttock without travelling as far down the leg. This distinction matters clinically, but as we said above, it’s not something we’re comfortable confirming from symptoms alone. NICE’s own guidance on assessing back pain and sciatica is built around exactly this: taking a careful history, ruling out red flags, and only then deciding what further assessment is actually needed.
If your pain is radiating, we’d want to see you sooner rather than later, not because it’s automatically an emergency, but because nerve-related pain that’s left unaddressed for too long can take longer to settle even once you do get the right treatment.
Kidney pain and lower left back pain from your spine can feel remarkably similar at first, but there are a few real differences worth knowing before you assume it’s “just your back.”
Kidney pain, from a stone or an infection, tends to sit deeper and further round toward your side, and it usually doesn’t change much whether you move, bend, or lie down. Mechanical back pain almost always does the opposite: it gets better or worse depending on your posture and movement, easing when you find a comfortable position and flaring with certain motions. Kidney-related pain also tends to come with other signals your spine wouldn’t produce on its own, like a fever, pain or burning when you urinate, or blood in your urine.
We’re not able to treat kidney conditions here, and we’d never want to give you the impression otherwise. If your pain doesn’t change with movement, or you notice any of those other symptoms, please see your GP or attend urgent care rather than booking with us, that’s the right next step for a suspected kidney issue, and we’ll say so plainly if we see you and suspect the same.

Left side back pain is serious enough to see a doctor urgently if it comes with fever, unexplained weight loss, numbness in the groin or inner thighs, loss of bladder or bowel control, or pain that wakes you repeatedly at night and doesn’t ease with rest.
These are what we call red flags, signs that something beyond an ordinary muscle or joint problem might be going on, and NICE’s own recommendations on back pain and sciatica are built specifically around screening for them early. If you have any of these, please go to your GP or A&E straightaway rather than waiting for a private appointment with us, this isn’t the kind of situation where a booking delay is worth the risk.
Outside of those red flags, here’s a simple way to think about timing. Pain that’s mild, eases within a week or two, and doesn’t radiate down your leg is reasonable to watch for a short while. Pain that’s still bothering you after two to three weeks, that’s getting worse rather than better, or that’s stopping you from working, sleeping, or exercising properly, is worth a proper assessment rather than more waiting. We see far too many patients who waited months hoping it would resolve on its own, when an accurate diagnosis early on would have meant a much shorter path back to normal.
The causes of back pain in lower left side that we see most often at RRMG fall into a handful of categories: facet joint irritation, SI joint dysfunction, disc-related pain, and muscular strain, sometimes with more than one contributing at once.
None of these need to be a mystery for long. Once we know which structure is driving your pain, we can talk through the treatment that fits your specific situation, rather than a generic plan aimed at “back pain” in the abstract.
We diagnose the source of your left-sided back pain by combining a thorough clinical history and physical exam with image-guided assessment, rather than relying on symptoms or a standard exam alone to tell us which structure is responsible.
This approach exists because of a real limitation in how back pain is usually assessed. As the research referenced earlier in this piece shows, ordinary clinical tests are weak at distinguishing disc, facet joint, and SI joint pain from each other, since all three can produce pain in a very similar location. We built our diagnose-first approach around that gap, using ultrasound and image guidance to see the affected structure directly, and where appropriate, using a targeted diagnostic injection to confirm exactly which joint or structure is generating your pain before recommending a treatment path.
This matters practically, not just academically. A treatment aimed at the wrong structure won’t help you, even if it’s the “correct” treatment for a similar-sounding condition. Confirming the source first is what lets us recommend something that’s actually likely to work for your specific pain, rather than the most common guess.
Non-surgical treatment for back pain lower left side at RRMG typically starts with the least invasive option that fits your diagnosis, and moves toward more targeted procedures only if that’s what your case needs.
Ultrasound-guided injections are often our first treatment step once we’ve confirmed the source of your pain. A precisely placed steroid injection can calm an inflamed facet or SI joint directly, giving you real relief while other approaches, like physiotherapy, have a chance to work on the underlying mechanics.
Radiofrequency ablation is a longer-lasting option for facet joint or SI joint pain that keeps returning after simpler treatments. It works by gently interrupting the small nerve signals carrying pain from that specific joint, and can provide relief that lasts considerably longer than a single injection, though it isn’t a permanent fix and pain can eventually return as those nerves regenerate.
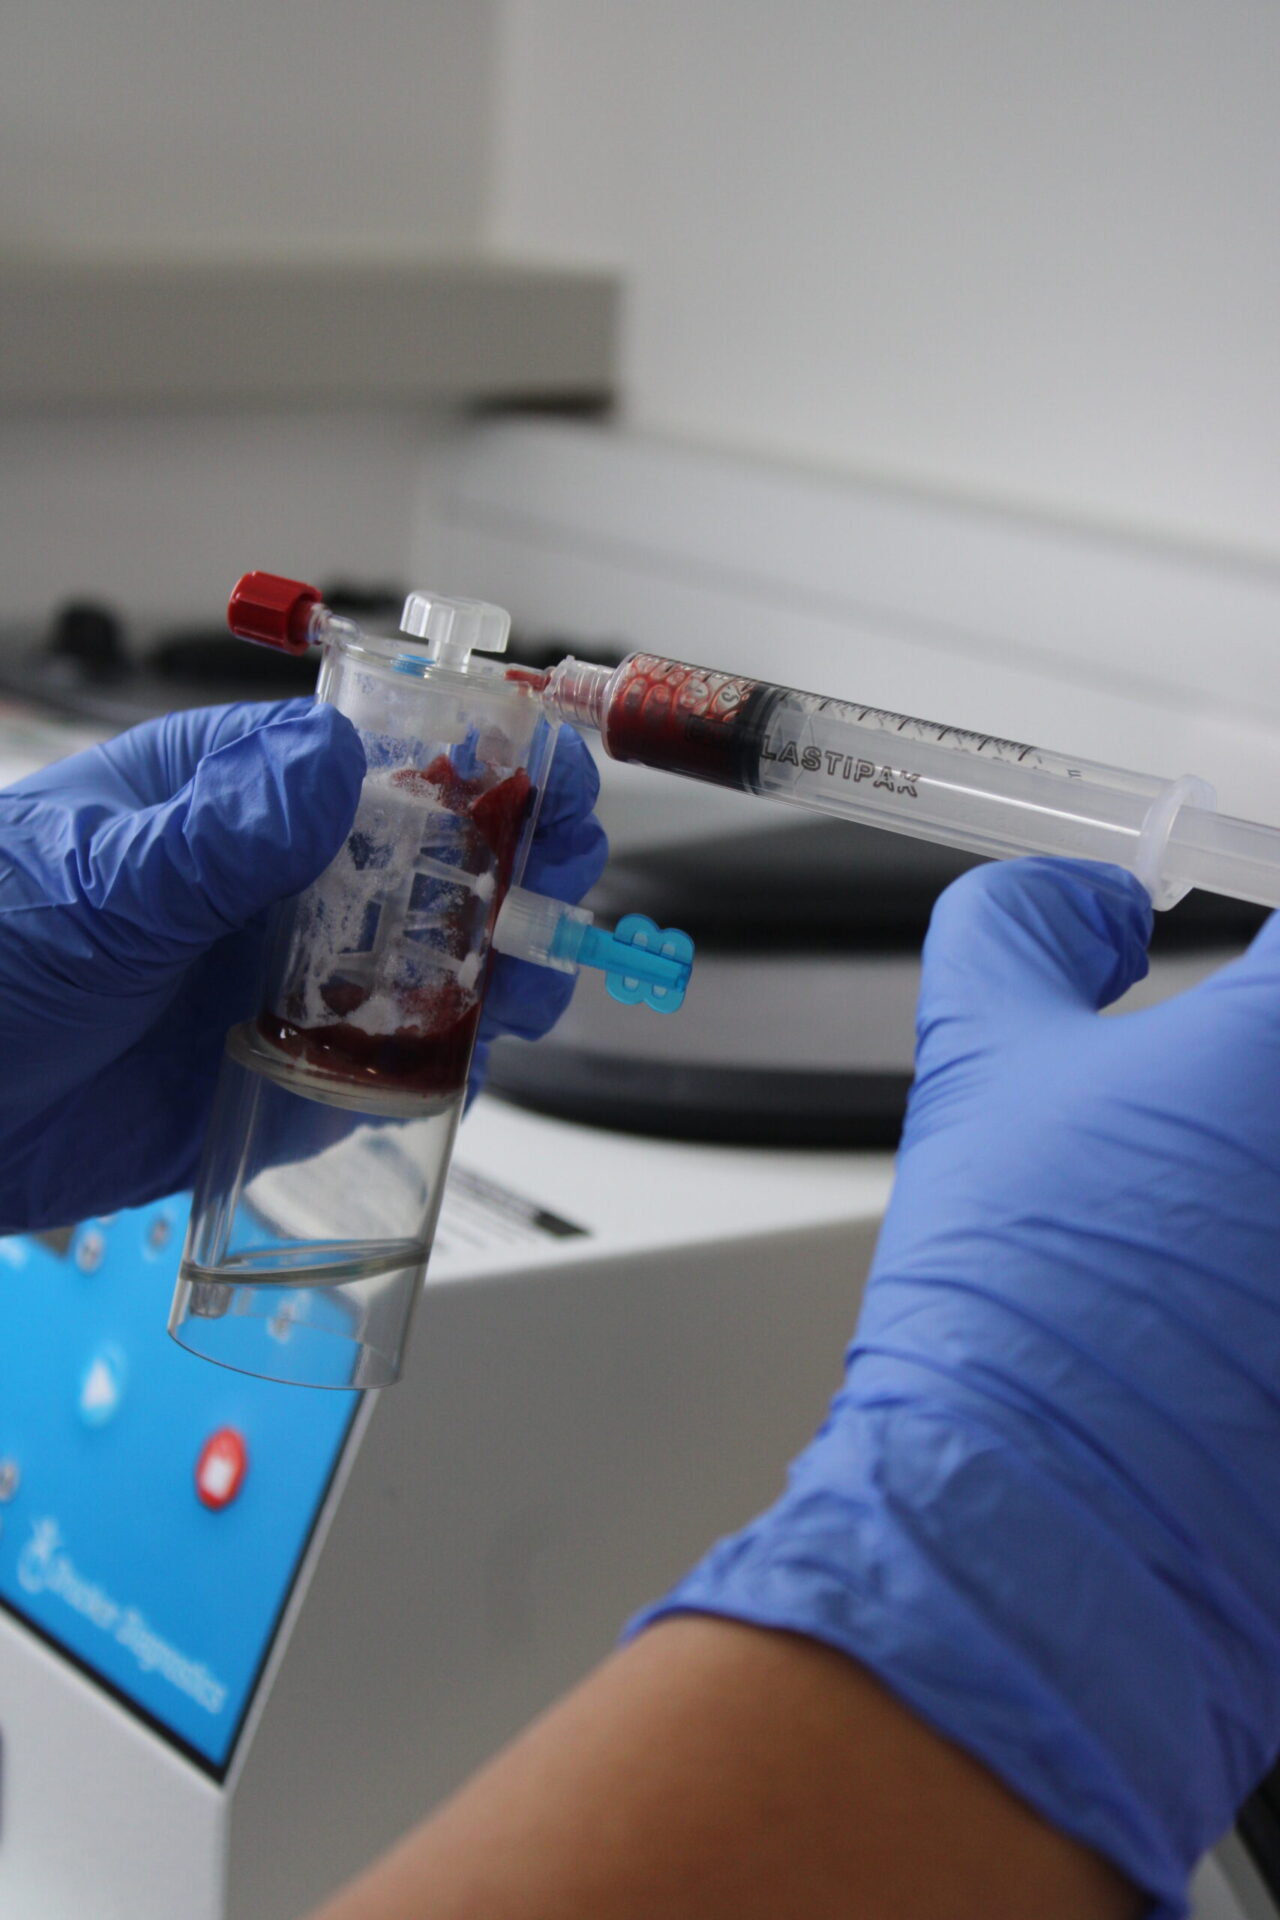
Regenerative options, including PRP (platelet-rich plasma), use your own blood’s healing components to support the body’s natural response in and around an irritated joint or disc. We’re careful never to suggest this “regrows” or “reverses” degeneration, what the evidence actually supports is a treatment designed to support the body’s own healing response, not a guaranteed structural fix.
For most of the mechanical causes described above, we’re able to offer a path that avoids surgery entirely, provided we get the diagnosis right first and start with an approach that matches what’s actually driving your pain.
Physical therapy and the right kind of movement play a real role alongside medical treatment for left-sided lower back pain, particularly once the acute discomfort has settled enough to move more freely.
Gentle movement and targeted exercises, guided by someone who understands which structure is involved, can help restore the mechanics that let your spine and pelvis share load evenly again rather than overloading one side. This is a real, useful part of your recovery, and we’re glad to see patients approach it that way. What we’d caution against is treating exercise on its own as a substitute for finding out what’s causing your pain in the first place. If the underlying joint or disc issue isn’t addressed, the same pattern of pain often returns even after weeks of dedicated stretching, because the mechanical cause behind it hasn’t changed.

Most lower left back pain is mechanical, from a muscle, joint, or disc, and isn’t a sign of something serious. It becomes a more urgent concern if it comes with fever, unexplained weight loss, numbness in the groin, loss of bladder or bowel control, or pain that consistently wakes you at night, in which case you should be seen promptly.
Mild lower back pain on the left side that eases within one to two weeks is usually nothing to worry about. Pain that persists beyond two to three weeks, worsens, or starts limiting your daily activities is worth a proper assessment rather than continued waiting, since an accurate diagnosis early on generally means a shorter path back to normal.
Stress can contribute to lower left back pain indirectly, mainly through muscle tension and poor posture that build up when you’re under sustained pressure. It’s very rarely the sole cause on its own, so if the pain persists, it’s still worth having the underlying mechanical structure properly assessed rather than attributing it to stress alone.
Muscular pain from a strain tends to ease with gentle movement and worsen with prolonged stillness, while joint-related pain, from a facet or SI joint, often has a more specific pattern tied to certain positions, like bending, twisting, or extending backward. Because these patterns can overlap, we confirm the source with image-guided assessment rather than relying on the pattern alone.
Not always. Many cases of lower left back pain can be assessed clinically and with ultrasound-guided examination without needing an MRI first. We’ll recommend imaging when your history or exam findings point clearly to something that needs it, rather than ordering it as a routine first step for every case.
If you’re asking why does the left side of my lower back hurt more than the right, it usually comes down to uneven load on one side, whether that’s from posture, repeated movement patterns, or a facet or SI joint on that side working harder than its counterpart. We’d want to see exactly which structure is carrying that extra load before suggesting a fix.
Left-sided lumbar pain without a clear injury still has a real cause, it’s just often a gradual one. Why left side back pain occurs this way usually traces back to a joint or disc that’s been under slightly more strain than the other side for weeks or months, until it finally becomes noticeable. An assessment can pinpoint which structure that is, even without a single obvious triggering event.
We’re RRMG, a private regenerative orthopaedics and sports medicine clinic on Blythe Road in London, founded by Dr Ralph Rogers, whose case we personally run from your first consultation through to treatment. We work with a wide range of insurance providers, as well as self-funding patients, so getting the right care shouldn’t come down to which pathway is easiest to find.
If you’ve read this far, you already know the tricky part about back pain lower left side: it can come from several different places, and guessing wrong means treating the wrong thing. That’s exactly the gap we exist to close. Instead of a long wait for an NHS referral followed by a generic diagnosis of “non-specific back pain,” we can usually see you quickly and give you a clear answer, drawing on founder Dr Ralph Rogers’s years of image-guided musculoskeletal work with elite athletes and everyday patients alike, about what’s causing your pain.
Once we know that, we’re confident in laying out the treatment options that fit your case, whether that’s a targeted injection, radiofrequency ablation, a regenerative option, or a simple course of physiotherapy. You don’t need to work out which one applies to you beforehand.
Booking is simple: reach out below, tell us what you’re experiencing, and we’ll take it from there. For current pricing on assessments and treatments, our fees page has the latest figures, consultations start from £215. We also treat a much wider range of conditions beyond back pain, and most of what we offer sits within our non-surgical treatment approach, so if something else has been bothering you too, it’s worth mentioning when you get in touch. You can read more about who we are and how we work before you book, if that’s helpful.
Dr Rogers has had a rich and illustrious career so far, which is continuing to grow and develop. Everything Ralph has been involved in since qualifying has added value to his knowledge and experience, but there have been some impressive highlights to note:
2018 – Present Founder Medical Director: Rogers Regenerative Medical Group (RRMG)
2012 – 2024 Medical Advisor – National Basketball Association
2008 – 2018 Medical Director: The London Sports Injury Clinic London
2010-2011 First Team Doctor, Chelsea Football Club
2007- 2010 The Football Association (Team Physician for England under 19 and development squads)
2005-2006 Medical Advisor: Trinidad & Tobago World Cup Football Team
2002 – 2008 Club Doctor: Walsall Football Club, West Midlands England
1998 – 2009 Medical Director: Medical & Orthopaedic Sports Therapy,
2000 – 2005 Sports Physician: Warwickshire County Cricket Club, Birmingham